The specialty of internal medicine has some of the most cognitively challenging aspects of any medical specialty. At the same time, it also has some of the greatest financial risk around billing. The very same complexity that creates a rich clinical experience in internal medicine (multiple chronic diseases, multiple comorbid conditions, complex coordination of care) directly complicates the process for obtaining accurate and consistent reimbursement for services rendered by the internist.
If your practice has felt as if you are working harder each year with less profit, you are not incorrect in your observations. The issue is rooted in the structure of our healthcare system, and the solution is achievable through effective internal medicine revenue cycle management.
Why Internal Medicine Revenue Cycle Management Is Uniquely Hard
Most specialties can rely on a relatively consistent range of billing options. For example, orthopedic practices usually only rely on procedure codes, while dermatology practices work from their own distinct “code family.” Internal medicine is distinct in that, on any one single encounter, you may have elements of E/M coding, chronic care management (CCM) billing, preventive services, interpretation of laboratory results, and coordination of care included in the encounter for billing purposes at different rates, all derived from different streams of documentation.
This creates the potential for tremendous revenue from internal medicine encounters, and it also creates a tremendous minefield for the practice doing the billing.
Internal medicine has a heavy emphasis on the assessment, and the management, of complex chronic conditions that often involve multiple organ systems (e.g., diabetes, heart failure, high blood pressure) and usually involve assessment and management of two or more chronic conditions in the same office visit. The focus of internal medicine is on cognitive services, chronic disease management, and coordination of care and, therefore, accurate E/M coding is especially critical when billing for these services. Inadequately capturing complexity in the documentation means the practice is reimbursed less than the true value of services provided.
Per the American Medical Association, physicians average nearly 2 hours of administrative time per hour of direct patient care, with 34% attributable to billing/insurance-related tasks. This ratio is not sustainable for internal medicine physicians managing panel sizes of 1,500 – 2,500 patients.
The Multi-Chronic-Condition Billing Problem
Here is a common example of an internal medicine visit: 67-year-old Medicare patient is seen for a 3-month interval visit who has Type II Diabetes with Nephropathy, Stage 3 CKD, Hypertension, Depression (History). Provider discusses medication adjustments and lab results; provider coordinates with Nephrology; provider updates care plan.
Each of these conditions must be supported with an ICD-10 code specific to that condition. The medical decision-making required to support a Level 4 or Level 5 E/M code are present, but will only be recognized if documentation captures it. A completed template note indicating “diabetes controlled, hypertension stable” does not support a 99214. In fact, it barely meets criteria for a 99213.
ICD-10 codes that have not been assigned correctly are found to lead to denial of services because of insufficient details within the claim submitted. Coding at a lower level for E/M services than is validated by the documentation decreases the amount of reimbursement received (e.g. coding 99213 instead of 99214 when the level of E/M service meets the criteria for 99214), and these errors are not isolated incidents, rather; they continue to happen every day within offices that have not matched their office documentation and billing cultures.
How Much Revenue Is Actually Being Lost?
According to the Medical Group Management Association (MGMA), coding errors and lost charges result in approximately 5% to 10% of revenue that should have been collected by physician’s practices, strictly due to coding errors and lost charges.
For example, a two-physician internal medicine office, that has projected yearly billings of $1,500,000, would lose between $75,000 and $150,000 each year due to administrative coding errors not from fraud, not from denied claims, just simply from coding that does not accurately represent what the physician completed in the patient encounter.
The E/M Coding Gap That’s Costing Internal Medicine Practices
The modifications to E/M service code levels created in the 2021 E/M Overhaul had a greater impact on the internal medicine specialty than other specialties. The development of a “time or medical decision making based” E/M service coding structure replaced the use of “the Key Component” method for coding E/M services and resulted in a decreased amount of required documentation to support the code level, but subsequently created a new level of uncertainty about how to document MDM in a way that is recognized by payors.
Undercoding as the Default As a standard, most physicians who treat internal medicine patients tend to bill for lower than what they should undercoding. They frequently code 99213 for patient visits when the documentation clearly allows for a higher code — 99214 or 99215. This isn’t because of fear or conservatism; it’s simply because no one has ever undertaken a systematic medical coding audit that would reveal their pattern.
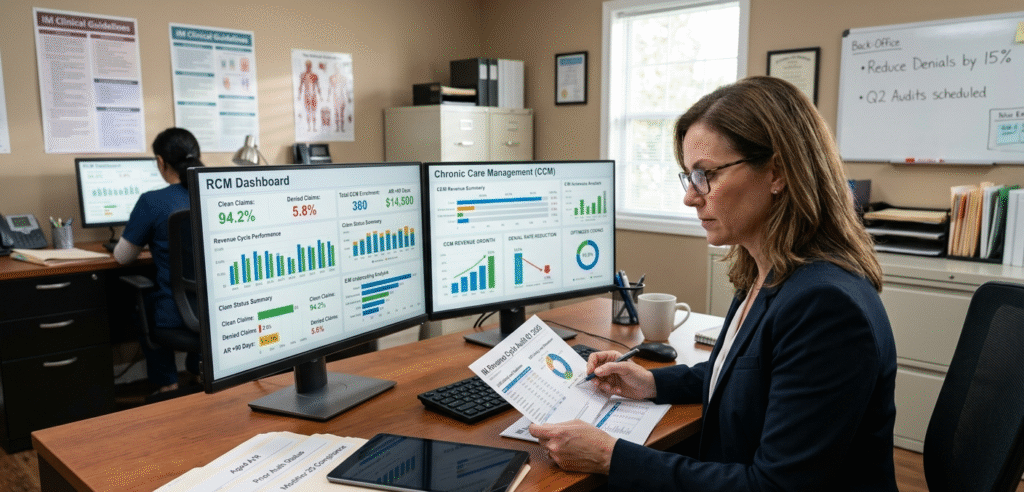
To get physicians to correct their habits, the best solution is to have ongoing coding audits, ideally on a quarterly basis. These audits compare the physician’s billed E/M level with the documentation supporting the level of medical decision making. Upon seeing the results of how their patterns compare to the coding guidelines, physicians generally correct their patterns immediately, and the overall revenue they recover is immediate.
The Modifier 25 Problem Nobody Warns You About
In many cases, patients receiving internal medicine treatment will receive both an annual preventive assessment as part of their routine visit and have a separate problem-focused visit during the same office visit. Therefore, in the case of those types of visits, you can bill both types of visits legitimately.
However, the information used in the above scenarios must support the use of Modifier 25 for the problem-focused office visit. Otherwise, when there is insufficient documentation, there will be a good chance that one of these types of visits may be denied by the payor. Internists that use the correct coding for services rendered at the point of care have a higher chance of receiving reimbursement for services rendered and for demonstrating compliance with preventive health care regulations.
Chronic Care Management: A Revenue Stream That Most Practices Undercollect
Chronic care management (CCM) codes are some of the most frequently underbilled services in the field of internal medicine. The Centers for Medicare and Medicaid Services (CMS) has established these codes in order to reimburse internists for time spent and for infrastructure costs accrued through managing patients with two or more chronic illnesses between office visit appointments. By properly billing for 99490, practices can receive an additional $40 to $80 for each Medicare patient with qualifying conditions, in addition to receiving reimbursements for their usual office visits.
For a practice with 500 Medicare patients who are managing patients with qualifying chronic care issues under CCM, the annual potential revenue for CCM billing would reach six figures; however, most internal medicine practices only collect a small percentage of this available revenue opportunity.
Why CCM Billing Falls Apart CCM codes are under increased scrutiny by payers due to previous violations of billing and documentation guidelines. Therefore, if time spent and/or notes related to care coordination are not adequately documented, the claims submitted for CCM may be rejected. Audit triggers are causing even more frequent delays in reimbursement.
Prior Authorization: The Administrative Burden Crushing Internal Medicine
According to the American Medical Association, physicians complete, on average, 39 requests for prior authorization each week in 2024. In a typical 5-day practice week, you will spend approximately 15-20 hours/week of staff time dedicated to completing prior authorizations in the internal medicine setting.
When authorizations are not handled correctly, claims can be denied (due to CO-15 error). If a 3-MD internal medicine group is not implementing an automated prior authorization tracking system, it will easily have 5–10 authorizations denied every week. This results in $750 to $3,000 lost revenue every week, for one process failure alone.
Accounts Receivable Aging: Where Internal Medicine Revenue Goes to Die
According to 2025 Medical Economics, over 40% of respondents reported that receiving reimbursement for services rendered takes more than two months. Because most internal medicine practices see a significant number of Medicare and Medicaid patients, this pattern causes large amounts of revenue to continue to be unpaid, which creates an ongoing issue related to Accounts Receivable (AR) Aging.
As per industry statistics, approximately 60% of claims that have been declined are not resubmitted. Decreased revenue or delayed payment should not be viewed solely as an AR concern. It is more accurate to view it as a workflow dilemma and/or denial management processes failing to deliver expected results.
How Internal Medicine Practices Can Fix Their Revenue Cycle
Channel your internal medicine practice’s revenue stream by utilizing tools that help fix existing problems.
Start with a Coding Audit A 90-day retroactive coding audit of the E/M level of each claim will determine where your revenue gap is. Internal medicine practices typically find that between 8% and 15% of visits were billed below the defensible level of care.
Redesign Documentation to Drive Billing Physicians do not have to think like billers; however, they do need to have clinical documentation practices that assist billers. By providing short documentation coaching sessions, physicians and their clinics will make long-term changes with minimal impact on patient care.
Outsource What You Can’t Staff Well According to an RCM Awareness study, greater than 50% of respondents indicated their organization needs to adapt quickly or they will not be able to improve their operations. Internal medicine practices that attempt to manage a complicated revenue cycle using a generalist billing staff continually perform worse than those who outsource to specialized medical billing services.
At The Medicators, we have continuously seen that when reviewing the financial performance of internal medicine practices, it is not that the practice fails to provide care; but rather the financial infrastructure does not support capturing the revenues related to care provided.
The Path Forward Is Cleaner Than It Looks
Internal Medicine practices do not lose revenue due to physician inexperience: they have a billing infrastructure that doesn’t support their clinical complexity. Change your documentation habits; conduct coding audits, create a formal revenue cycle management (CCM) system; monitor and manage denials daily partner with an expert if needed.
FAQ: Internal Medicine Revenue Cycle Management
Why do internal medicine practices struggle more with billing than other specialties?
Because of the wide variety of services offered E/M, CCM, preventive care, chronic disease management there are more documentation and coding requirements.
What is the most common reason internal medicine claims get denied?
According to billing data, the most frequent source cited was either unspecified ICD-10 codes, under-documented E/M levels, or the lack of a prior authorization.
How much revenue can CCM billing add to an internal medicine practice?
If your practice has 500 qualifying Medicare patients, earning $40–$80 per month can equate to an annual increase of over $100,000 in cash flow.
How often should internal medicine practices audit their coding?
Coding audits should be performed on at least a quarterly basis to prevent coding drift.
Should small internal medicine practices outsource their RCM?
Independent practices typically achieve superior performance against in-house billing from a cost and denial rate perspective when using a specialized partner.