
Every month, thousands of claims leave your billing department and never come back as payments. Some get bounced before they even reach the insurance company. Others sail through the front door, only to be turned away at the payer’s desk weeks later.
If your team treats these two situations the same way, you are probably losing revenue without knowing why.
Denial rate and rejection rate sound like interchangeable billing jargon, but they describe two completely different failure points in the claims process. Confuse them, and your practice ends up fixing the wrong problem, chasing the wrong reports, and bleeding cash flow month after month.
This guide breaks down exactly what separates a rejected claim from a denied claim, why the distinction matters for your bottom line, and what your practice can do today to bring both numbers down. By the end, you will know precisely where your claims are getting stuck and how to fix it.
Understanding the Medical Claims Process
Before comparing the two metrics, it helps to see where each one actually occurs. A claim does not go from “treatment” to “payment” in one step. It moves through a full workflow, and rejections and denials sit at very different points along that path.
A typical claims journey looks like this:
- Patient registration
- Insurance verification
- Medical documentation
- Medical coding (CPT, ICD-10-CM, HCPCS)
- Charge entry
- Claim scrubbing
- Claim submission
- Clearinghouse validation
- Payer adjudication
- Payment posting
- Denial management
- Accounts receivable follow up
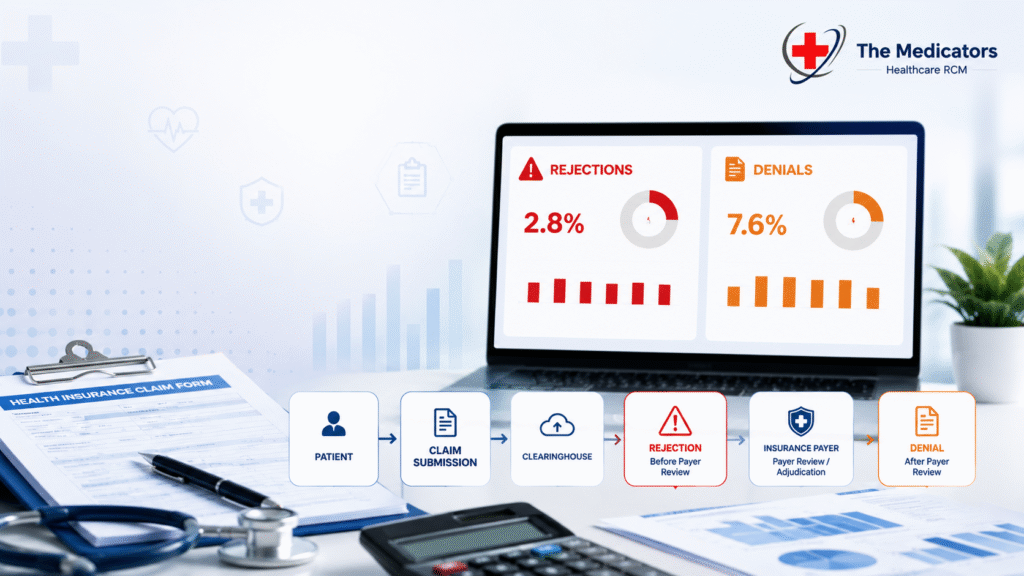
Here is the part most billing staff miss: rejections happen before payer adjudication, while denials happen after it. That single sentence explains almost every difference discussed in this article. If a claim never makes it past the clearinghouse gate, it is rejected. If the insurance company reviews it and refuses to pay, it is denied.
What Is a Claim Rejection?
A claim rejection happens when a claim is kicked back before the insurance payer ever evaluates it for payment. It has not been accepted into the system for review at all, which means it has not technically been “processed” in the eyes of the payer.
Rejections typically occur at the clearinghouse level or through the payer’s front end edits, long before a claims examiner looks at the medical details. They are usually caused by something mechanical: a missing digit in a policy number, a mismatched name, an invalid code format, or a field left blank.
Characteristics of a Rejected Claim
- It never enters adjudication, so no payment decision has actually been made
- It can usually be corrected and resubmitted within a day or two
- It is almost always caused by technical or formatting errors rather than clinical ones
- It does not require an appeal, just a correction
Think of a rejection as a returned envelope. The post office refused delivery because the address was wrong, not because the recipient rejected the letter.
What Is a Claim Denial?
A claim denial is very different. The claim actually reached the payer, went through adjudication, and was formally reviewed. The insurance company looked at the medical necessity, the coverage terms, and the policy rules, then decided not to pay part or all of the claim.
Denials happen after the payer has made a decision, which is the key difference from a rejection. The insurer might cite a lack of medical necessity, a missing prior authorization, an expired filing window, or a coding mismatch between diagnosis and procedure.
Characteristics of a Denied Claim
- The claim reaches full payer review before being turned down
- The payer evaluates it against medical necessity and policy requirements
- Resolving it usually requires an appeal, additional documentation, correction and resubmission, or in some cases a write off
- It carries a heavier administrative and financial burden than a rejection
If a rejection is a returned envelope, a denial is a letter that was opened, read, and sent back with a rejection note attached.
Denial Rate vs Rejection Rate: Key Differences
| Feature | Claim Rejection | Claim Denial |
|---|---|---|
| Occurs | Before adjudication | After adjudication |
| Who identifies it | Clearinghouse or payer front end edits | Insurance payer |
| Claim status | Not processed | Processed but not paid |
| Primary cause | Technical or data errors | Coverage, coding, documentation, or policy issues |
| Can be resubmitted? | Usually yes, quickly | Often requires a formal appeal or correction |
| Financial impact | Short term delay | Greater revenue risk |
| Resolution time | Usually shorter | Often longer |
A rejection is a paperwork problem. A denial is a decision. That distinction should shape how your billing team prioritizes its time: rejections need quick fixes and resubmission, while denials need investigation, documentation, and sometimes a formal appeal process.
What Is Claim Rejection Rate?
Rejection rate measures the percentage of submitted claims that bounce back before ever reaching the payer for review. It is calculated as:
Rejection Rate = (Number of Rejected Claims ÷ Total Claims Submitted) x 100
Practices should track this number closely because it is an early warning signal. A high rejection rate points to weak front end processes, whether that is registration errors, poor eligibility checks, or outdated claim scrubbing rules. Most well run practices aim to keep rejection rates in the low single digits, and anything above that range usually points to a fixable process gap rather than a payer issue.
Rejection rate also feeds directly into your first pass acceptance rate, since every rejected claim lowers the percentage of claims accepted correctly on the first attempt.
What Is Claim Denial Rate?
Denial rate measures the percentage of adjudicated claims that the payer refuses to pay, in full or in part. The formula is:
Denial Rate = (Number of Denied Claims ÷ Total Claims Submitted) x 100
This metric matters even more for long term financial health, because denied claims represent revenue that has already gone through the full billing cycle before falling through. According to industry benchmarks tracked by organizations like the <cite index=”0-1″>Healthcare Financial Management Association</cite>, a denial rate under 5 percent is generally considered healthy, while rates climbing past 10 percent signal serious revenue cycle problems.
A high denial rate does not just cost money on the claims themselves. It multiplies staff hours spent on appeals, delays cash flow, and can quietly train payers to expect pushback on future claims.
Why Both Metrics Matter in Revenue Cycle Management
Tracking only one of these numbers gives you half the picture. Together, rejection rate and denial rate tell you:
- Revenue protection: Both metrics represent money that has not yet reached your bank account
- Cash flow: Rejections delay payment by days, denials can delay it by months
- Billing efficiency: High numbers on either side mean staff are reworking claims instead of processing new ones
- Staff productivity: Every resubmission or appeal takes time away from other revenue generating tasks
- Patient satisfaction: Billing errors and delays often surface as confusing statements or surprise bills for patients
- Practice profitability: Left unmanaged, both metrics quietly erode margins over time
This is exactly the kind of pattern our team studies inside every revenue cycle management engagement. Fixing one metric without watching the other rarely solves the underlying cash flow problem.
Common Reasons Claims Are Rejected
Most rejections trace back to details that should have been caught before the claim ever left your building.
Incorrect patient demographics. A misspelled name or wrong date of birth is enough to trigger an automatic bounce.
Invalid insurance information. Outdated policy numbers or group IDs stop a claim before it starts.
Missing subscriber details. If the claim does not clearly identify the policyholder, it gets flagged instantly.
Incorrect NPI. A wrong or mistyped National Provider Identifier is a common, entirely avoidable rejection cause.
Invalid Tax ID. Mismatched tax identification numbers are an easy trigger for automatic edits.
Incorrect Payer ID. Sending a claim to the wrong payer routing code guarantees a bounce.
Duplicate claims. Submitting the same claim twice, often by accident, triggers an automatic rejection.
Missing required fields. Blank fields that a payer’s system expects will stop the claim cold.
Invalid CPT codes. Using outdated or retired procedure codes causes an immediate edit failure. The <cite index=”1-1″>American Medical Association</cite> updates CPT code sets annually, so outdated code books are a frequent culprit.
Invalid ICD-10-CM codes. The same applies to diagnosis codes that are incomplete or no longer valid.
Missing modifiers. Codes like modifier 25 or modifier 59 clarify distinct services, and leaving them off triggers front end edits.
Invalid Place of Service (POS). A mismatched POS code compared to the billed service raises an automatic flag.
Clearinghouse formatting errors. Improper file formatting at the clearinghouse level is a purely technical, and entirely preventable, rejection cause.
Missing authorization numbers. If a service required prior approval and the number is missing from the claim, it gets rejected on the spot.
Expired insurance coverage. Submitting a claim for a policy that lapsed before the date of service is an automatic bounce.
Claim scrubbing software catches most of these issues before submission, running each claim through payer specific edits and flagging errors while there is still time to fix them. This is precisely why practices that invest in strong medical billing services see dramatically lower rejection rates than those relying on manual review alone.
Common Reasons Claims Are Denied
Denials are usually rooted in clinical, coverage, or policy issues rather than data entry mistakes.
Lack of medical necessity. The payer determines the documented diagnosis does not support the billed service.
Prior authorization not obtained. A required approval was never secured before the service was rendered.
Non-covered services. The plan simply does not include the billed service under its coverage terms.
Incorrect diagnosis-procedural linkage. The ICD-10 code does not logically connect to the CPT code billed.
Documentation deficiencies. Clinical notes do not sufficiently support the level of service billed.
Timely filing limit exceeded. The claim was submitted after the payer’s deadline, which varies by payer and plan.
Coordination of Benefits (COB) issues. The payer believes another insurer should be billed first.
Duplicate billing. The same service was billed more than once for the same date.
Frequency limit violations. The service was billed more often than the plan allows within a set period.
Experimental or investigational services. The payer classifies the treatment as outside standard coverage.
Eligibility issues discovered during adjudication. Coverage had already lapsed by the time the payer reviewed the claim.
Payer policy violations. The service does not align with that specific payer’s internal coverage rules.
Unlike rejections, most of these require deeper investigation, supporting documentation, and often a formal appeal, which is why denial management usually involves a specialized team rather than a quick resubmission.
Financial Impact of Rejections vs Denials
Both metrics drain revenue, but they do it differently.
Rejections create delayed reimbursements, increased administrative costs, and higher staff workload, since every rejected claim has to be pulled, corrected, and resubmitted manually.
Denials go further, contributing to cash flow interruptions, revenue leakage, and a growing accounts receivable (A/R) backlog. Left unresolved, denied claims frequently convert into write offs, directly reducing practice profitability.
The Centers for Medicare and Medicaid Services notes that <cite index=”2-1″>claims processing accuracy directly affects program integrity and provider reimbursement timelines</cite>, which underscores why both front end and back end claim accuracy carry real financial weight, not just administrative annoyance.
How Claim Rejections Affect Healthcare Practices
A rising rejection rate slows down claim submission across the board, since staff must stop and correct errors instead of moving forward with new claims. This creates extra administrative work, lowers your clean claim rate, and ultimately delays payments even on claims that would otherwise have been paid without issue.
How Claim Denials Affect Healthcare Practices
Denials carry heavier consequences. Practices lose staff hours to appeals, absorb lost revenue on claims that are never successfully overturned, and face higher collection costs chasing aged accounts. Over time, this creates provider frustration and can even complicate patient billing when balances get passed downstream.
How to Reduce Claim Rejections
- Improve patient registration. Double check names, dates of birth, and policy numbers at every visit.
- Verify insurance eligibility before each appointment, not just at intake. Our eligibility verification services are built specifically to catch coverage gaps before a claim is ever created.
- Use claim scrubbing software to catch formatting and coding errors automatically.
- Validate CPT, ICD-10-CM, and HCPCS codes against current code sets before submission.
- Check modifiers for accuracy on every applicable claim.
- Review demographic accuracy as a standard part of your intake workflow.
- Update payer rules regularly, since front end edits change often.
- Train billing staff continuously on new payer requirements and coding updates.
How to Reduce Claim Denials
- Improve documentation so clinical notes clearly support billed services.
- Strengthen medical coding accuracy through regular internal review.
- Obtain prior authorizations before services are rendered, not after.
- Perform internal coding audits on a recurring schedule.
- Monitor payer policy changes as they are announced.
- Appeal denials promptly, since most payers enforce strict appeal windows.
- Analyze denial trends to catch recurring root causes early.
- Improve clinical documentation at the point of care, not after the fact.
A recurring billing audit is one of the fastest ways to catch the coding and documentation patterns quietly driving your denial rate up.
Claim Scrubbing vs Denial Management
| Claim Scrubbing | Denial Management |
|---|---|
| Prevents errors | Resolves payer decisions |
| Happens before submission | Happens after adjudication |
| Improves clean claim rate | Improves revenue recovery |
| Focuses on prevention | Focuses on correction |
Both functions work together as two halves of the same system. Scrubbing stops rejections before they happen, while denial management recovers revenue after a payer has already made a decision. A practice that only invests in one half of this equation will always be leaving money on the table.
Key Revenue Cycle Metrics Every Practice Should Track
| KPI | Why It Matters |
|---|---|
| Clean claim rate | Measures the quality of claims at first submission |
| First pass acceptance rate | Indicates overall billing accuracy |
| Claim rejection rate | Shows front end claim quality |
| Claim denial rate | Measures payer approval success |
| Days in accounts receivable (A/R) | Tracks how quickly claims turn into payments |
| Net collection rate | Measures how much allowed revenue is actually captured |
| Appeal success rate | Evaluates how effectively denials are recovered |
Consistent tracking of these KPIs is one of the clearest indicators of a healthy revenue cycle, and it is exactly what our AR management services monitor for clients on an ongoing basis.
Technology That Helps Reduce Rejections and Denials
- Claim scrubbing software that flags errors before submission
- Revenue cycle management platforms that centralize claim tracking
- Clearinghouses that apply payer specific front end edits
- AI assisted coding tools that catch mismatches between diagnosis and procedure
- Eligibility verification tools that confirm coverage in real time
- Electronic health records (EHR) that standardize documentation
- Billing analytics dashboards that surface trends before they become expensive
Best Practices to Maintain Low Rejection and Denial Rates
- Keep patient registration accurate at every single visit
- Verify insurance before every visit, not just the first one
- Use current CPT and ICD-10-CM code sets
- Review documentation thoroughly before submission
- Track payer policy updates as they are published
- Audit claims on a regular schedule
- Monitor KPIs monthly rather than quarterly
- Train billing staff continuously, since payer rules shift often
- Automate claim scrubbing wherever possible
- Review recurring denial patterns to catch systemic issues early
Warning Signs Your Practice Has Billing Performance Issues
- Rejection rates that keep climbing month over month
- Denial rates trending upward instead of down
- Rising accounts receivable with no clear explanation
- Reimbursements consistently arriving later than expected
- A growing backlog of claim corrections
- Frequent, repetitive correspondence from payers
- Collections that decline despite steady patient volume
If any of these sound familiar, it is worth a closer look at your current process before the numbers get worse.
How Professional Medical Billing Services Reduce Rejections and Denials
This is where an experienced billing partner earns its keep. A well run RCM team combines several layers of protection that most in house teams simply do not have the bandwidth to maintain:
- Certified medical coders who stay current on CPT, ICD-10-CM, and HCPCS changes
- Advanced claim scrubbing tuned to payer specific edits
- Payer specific billing expertise built over years of direct experience
- Documentation reviews that catch gaps before a payer ever sees the claim
- Eligibility verification completed before every scheduled visit
- Prior authorization management so approvals are secured ahead of service
- Denial appeals handled by staff who understand payer appeal windows and requirements
- Ongoing revenue cycle monitoring across every stage of the claims process
- Transparent performance reporting so you always know where your numbers stand
- Continuous compliance updates as payer and regulatory rules shift
Why Choose The Medicator’s for Medical Billing Services
Understanding the difference between denial rate and rejection rate is only useful if your practice has the systems in place to act on it. That is exactly where The Medicator’s steps in.
Our certified medical billing and coding specialists combine advanced claim scrubbing technology with payer specific compliance expertise to catch errors before they ever leave your office. We handle proactive denial prevention alongside accurate coding and documentation review, so fewer claims fall through either gap in the first place.
When something does slip through, our comprehensive denial management and appeals process goes to work immediately, backed by transparent KPI reporting so you always know exactly where your practice stands. Combined with end to end revenue cycle management support, the result is consistently reduced rejection and denial rates, along with stronger, more predictable cash flow.
Conclusion
Claim rejections and claim denials are not the same problem, and treating them that way is one of the most common (and most expensive) mistakes in medical billing. Rejections are usually technical or data entry errors that occur before a payer ever reviews the claim, while denials happen after full adjudication due to coverage, coding, documentation, or policy issues.
Monitoring both metrics closely, tightening your front end processes, and strengthening your back end denial management all work together to protect your revenue. Practices that track these numbers consistently, and partner with experienced billing professionals when the workload outgrows their internal team, see fewer claim delays, healthier cash flow, and stronger long term profitability.
If your practice is struggling to keep rejection and denial rates under control, our team can walk through your current numbers and show you exactly where the leaks are. Request a free practice analysis or get in touch with our team to see how a dedicated revenue cycle partner can turn these metrics around.
Frequently Asked Questions
What is the difference between a denied claim and a rejected claim?
A rejected claim never reaches the payer for review, usually due to a technical error. A denied claim reaches the payer, goes through adjudication, and is formally refused.
Which is worse: a denial or a rejection?
Denials generally carry a heavier financial and administrative burden, since the claim has already gone through the full billing cycle before being refused.
Can a rejected claim become a denied claim?
Not directly. Once corrected and resubmitted, a previously rejected claim enters adjudication for the first time and could then be approved or denied based on payer review.
Can denied claims be appealed?
Yes. Most payers allow a formal appeal process, though timelines and documentation requirements vary by payer and plan.
How is rejection rate calculated?
Rejection rate equals the number of rejected claims divided by total claims submitted, multiplied by 100.
How is denial rate calculated?
Denial rate equals the number of denied claims divided by total claims submitted, multiplied by 100.
What is a good denial rate?
Most industry benchmarks consider a denial rate under 5 percent to be healthy for a well run practice.
What is a good rejection rate?
Rejection rates in the low single digits generally indicate strong front end billing processes.
How does claim scrubbing reduce rejections?
It reviews claims against payer specific edits before submission, catching formatting and coding errors while there is still time to fix them.
How can practices reduce claim denials?
Stronger documentation, accurate coding, timely prior authorizations, and prompt appeals all help lower denial rates over time.
What KPIs should medical practices monitor?
Clean claim rate, first pass acceptance rate, rejection rate, denial rate, days in A/R, net collection rate, and appeal success rate.
Why are claims rejected before adjudication?
Because the clearinghouse or payer’s front end system flags a technical, formatting, or eligibility issue before the claim ever reaches a claims examiner for review.








